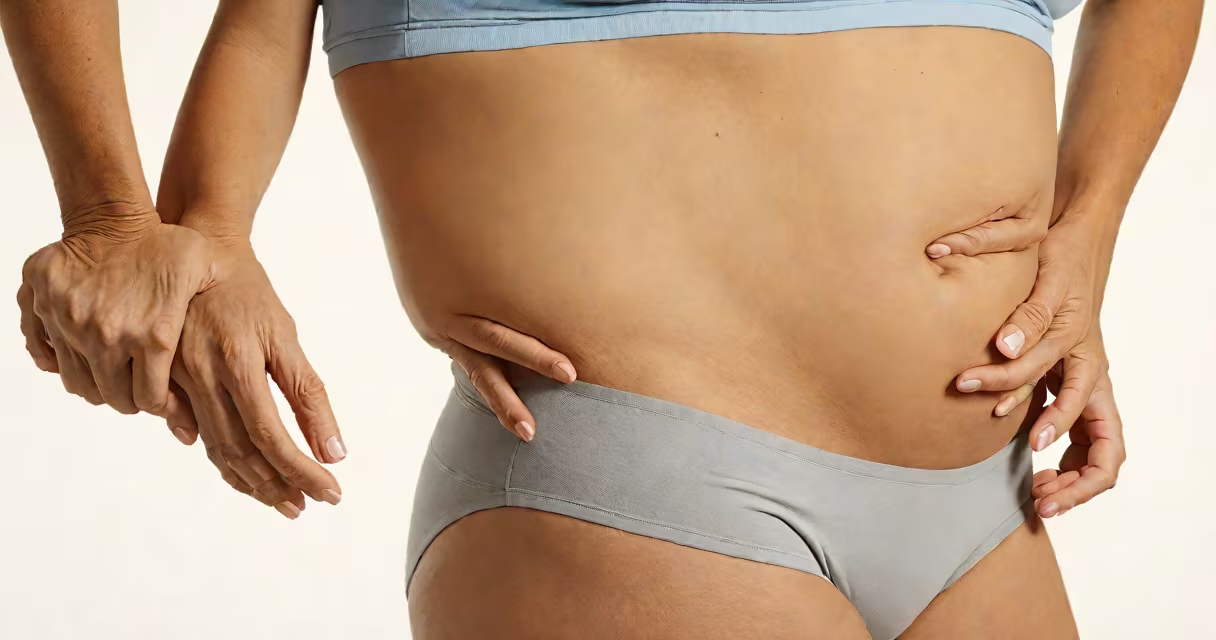
Diastasis recti stomach bulge refers to a visible protrusion in the center of the abdomen caused by the separation of the rectus abdominis muscles, which normally run vertically along the midline. This condition commonly develops during pregnancy due to increased intra-abdominal pressure but can also occur in men, infants, or individuals who perform heavy lifting incorrectly.
The separation happens when the linea alba-the connective tissue running between the two halves of the abdominal wall-stretches beyond its normal capacity. A bulge becomes apparent when the abdominal muscles pull apart, especially during activities that increase abdominal pressure, such as sitting up from lying down or coughing. The gap typically measures 2.5 cm or wider to qualify as diastasis recti, according to the American Physical Therapy Association (APTA).
Not all abdominal protrusions are diastasis recti. Some people mistake a soft, rounded belly after childbirth for diastasis, but the underlying cause may be excess fat, weakened obliques, or poor posture. True diastasis recti involves actual muscle separation, not just soft tissue displacement. A physical exam or ultrasound can confirm the diagnosis.
During pregnancy, hormonal changes-particularly relaxin-soften connective tissues, allowing the abdominal wall to stretch. As the uterus expands, the rectus abdominis muscles are pushed apart. This stretching can persist postpartum if the muscles don't regain their tension through targeted rehabilitation.
Even without pregnancy, diastasis recti can develop from repetitive strain. Heavy weightlifting with improper form, chronic constipation, or excessive abdominal exercises like crunches can overstretch the linea alba. The condition is more common in people with higher body mass index (BMI), but it's not limited to those categories.
A 2021 study published in *The Journal of Women's Health* found that 60% of women had measurable diastasis recti six weeks postpartum, though many didn't report symptoms. This highlights that the condition can exist without pain or discomfort, making self-assessment unreliable.
Diastasis recti is classified by the width of the gap and the depth of the separation. The most widely used assessment tool is the finger-width test, where clinicians measure how many fingers fit into the gap between the abdominal muscles.
| Severity Level | Gap Width | Depth of Separation | Functional Impact |
|---|---|---|---|
| Mild | 1-2 fingers | Shallow | Minimal impact on core function |
| Moderate | 2-3 fingers | Medium depth | Noticeable bulge during movement |
| Severe | 4+ fingers | Deep, often with tissue herniation | Increased risk of hernia, pelvic floor dysfunction |
One non-obvious distinction: a visible bulge does not always correlate with gap size. Some individuals have wide separations but minimal outward appearance due to strong surrounding musculature. Conversely, others show a pronounced bulge with only a small gap, indicating weak transverse abdominis activation.
Ultrasound imaging provides a more accurate measurement than manual testing. A 2019 study in *Physical Therapy* showed that manual assessments overestimated gap width by up to 1.5 cm compared to ultrasound results, underscoring the need for clinical confirmation.
Many assume that diastasis recti stomach bulge is purely cosmetic. In reality, it can impair core stability, contribute to lower back pain, and worsen pelvic floor issues. The American College of Obstetricians and Gynecologists (ACOG) notes that untreated diastasis may lead to long-term functional limitations, including difficulty lifting objects or maintaining balance.
Another frequent error is using abdominal exercises like sit-ups or planks to "fix" the bulge. These movements increase intra-abdominal pressure and can deepen the separation. Instead, evidence-based approaches focus on activating the transverse abdominis-the deepest abdominal layer-through controlled breathing and neuromuscular re-education.
I once observed a client who had completed multiple fitness programs claiming to "fix her core." She performed hundreds of daily crunches and still had a 4-finger gap. After switching to a structured rehabilitation protocol under a physical therapist, she reduced the gap to 1.5 fingers within eight weeks and eliminated the bulge during functional tasks.
Non-surgical management is effective for most cases. A 2020 randomized trial in *BJOG: An International Journal of Obstetrics & Gynaecology* found that 85% of participants with mild-to-moderate diastasis recti improved after 12 weeks of targeted exercise, including diaphragmatic breathing, pelvic tilts, and dead bugs.
Key elements of recovery include:
Surgical intervention is rare and reserved for severe cases with persistent symptoms despite conservative treatment. Procedures like component separation or mesh reinforcement are considered only when quality of life is impaired.
Diastasis recti stomach bulge is not a permanent condition. With correct guidance and consistent effort, muscle alignment can improve. Early intervention yields better outcomes, especially within the first year postpartum. Awareness and proper assessment are critical steps toward restoring core integrity and reducing long-term complications.