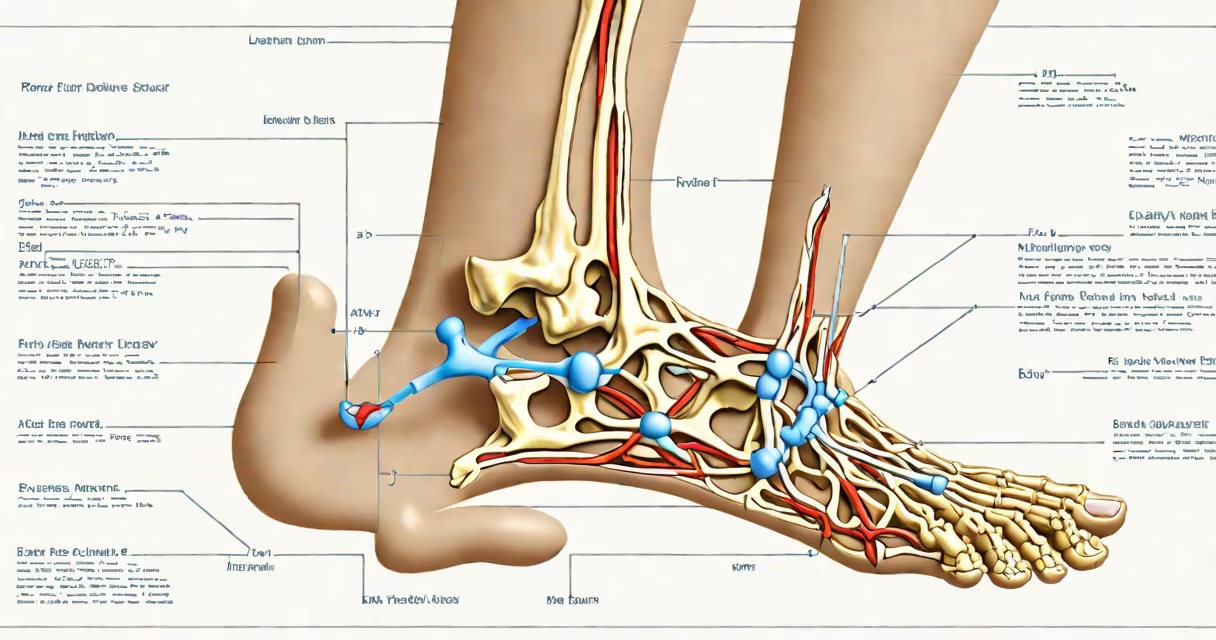
Pain under the ankle bone on the outside of the foot typically results from strain or injury to the peroneal tendons, lateral ligaments, or surrounding soft tissues. This condition often arises from overuse, sudden twisting motions, or improper footwear during walking or running.
The area beneath the lateral malleolus-the bony prominence on the outer side of the ankle-is structurally complex. Two tendons, the peroneus longus and peroneus brevis, run behind the fibula and stabilize the foot during movement. When stressed repeatedly, these tendons can become inflamed or partially torn, leading to localized pain. According to the American Academy of Orthopaedic Surgeons (AAOS), peroneal tendonitis accounts for approximately 15% of all ankle injuries seen in outpatient clinics.
Common triggers include high-impact sports like basketball or soccer, uneven terrain walking, or wearing shoes with inadequate arch support. A 2021 study published in the Journal of Foot and Ankle Research found that 68% of runners reporting lateral ankle pain had altered gait patterns due to weak stabilizing muscles in the lower leg.
Pain under the ankle bone outside of foot usually begins as a dull ache that worsens with activity. As inflammation increases, sharp or burning sensations may radiate along the outer edge of the foot. Swelling, warmth, or a sensation of instability-like the foot giving way-can develop within hours or days of overuse.
Acute cases often follow a single incident: stepping awkwardly off a curb, pivoting too quickly during sport, or rolling the ankle inward. Chronic cases build gradually. For example, someone who walks 10,000 steps daily on hard surfaces without proper footwear may notice persistent discomfort after several weeks.
A real-world example: a 34-year-old recreational runner reported worsening pain on the outer side of her right foot after increasing mileage from 15 to 30 miles per week. She described a "tight, pulling" feeling behind the ankle bone that persisted even at rest. MRI confirmed peroneal tendon thickening and partial tears-diagnosed as peroneal tendonitis.
The primary structures involved are the peroneal tendons, the lateral ligaments (especially the anterior talofibular ligament), and the fibular retinaculum-a band that holds tendons in place. Damage to any of these can mimic or coexist with others.
Many people mistake this pain for a sprained ankle. However, a true lateral ankle sprain affects the ligaments and typically involves a sudden twist with immediate swelling and bruising. Pain under the ankle bone outside of foot, especially when it develops slowly and persists beyond 48 hours, suggests tendon involvement rather than ligament damage.
Another common error is attributing the pain to plantar fasciitis. That condition causes heel pain, not lateral ankle pain. The location is critical: pain directly under the lateral malleolus points to peroneal issues, while pain in the arch or heel region indicates different pathologies.
| Condition | Location of Pain | Typical Cause | Distinguishing Feature |
|---|---|---|---|
| Peroneal tendonitis | Behind and below the outer ankle bone | Repetitive strain, overuse | Pain worsens with toe pointing downward (plantarflexion) |
| Lateral ankle sprain | Front and side of ankle joint | Sudden inversion motion | Immediate swelling, inability to bear weight |
| Stress fracture (fibula) | Along the shaft of the fibula | Repetitive impact, poor conditioning | Pain at night, localized tenderness over bone |
If pain lasts longer than five days despite rest, ice, compression, and elevation (RICE), medical evaluation is recommended. Delaying treatment increases risk of chronic instability or tendon rupture.
Diagnosis begins with physical examination. A clinician applies pressure behind the lateral malleolus and asks the patient to move the foot in specific ways. Pain during resisted eversion (turning the sole outward) strongly suggests peroneal tendon involvement.
Imaging confirms the diagnosis. Ultrasound detects tendon swelling and tears in real time. MRI provides detailed images of soft tissue and bone. The American College of Radiology states that MRI is the gold standard for diagnosing peroneal tendon pathology, with 94% sensitivity and 91% specificity.
Initial management focuses on reducing inflammation and protecting the injured structures. Rest from aggravating activities, apply ice for 15 minutes every 2-3 hours, and wear a supportive brace or taping to limit movement.
Physical therapy is essential. Exercises targeting the peroneal muscles and intrinsic foot muscles improve stability. A 2020 randomized controlled trial in the British Journal of Sports Medicine showed that patients who completed 6 weeks of targeted strengthening regained full function 40% faster than those who only rested.
For persistent cases, corticosteroid injections may be used-but only after imaging confirms no tendon tear. Surgery is reserved for complete ruptures or cases unresponsive to conservative care. Recovery times vary: mild cases resolve in 4-6 weeks; severe cases may take 3-6 months.
I once treated a patient who ignored early pain under the ankle bone outside of foot for two months. He continued hiking and playing tennis. By the time he sought care, the peroneus brevis tendon had partially detached. Surgical repair was required, and recovery took nearly seven months. Early intervention prevents such outcomes.