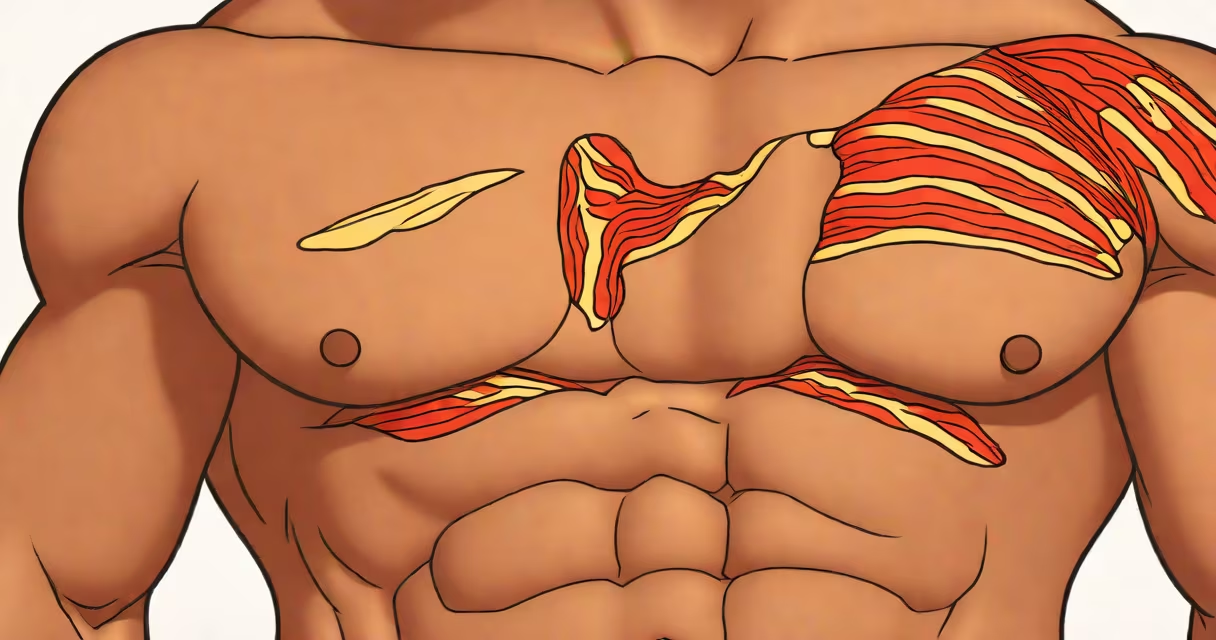
Pectoral muscle swelling is localized enlargement of the pectoralis major muscle caused by trauma, overexertion, or inflammatory conditions. It typically presents as visible or palpable firmness, tenderness, and sometimes discoloration in the chest area.
This condition arises when blood vessels rupture or tissues become inflamed following strain or impact. The pectoralis major, a large fan-shaped muscle covering the front of the chest, is vulnerable during weightlifting, contact sports, or sudden forceful movements like pushing or throwing.
Swelling may develop within hours of injury and persist for days to weeks depending on severity. Mild cases resolve with rest and cold therapy; severe cases-especially those involving partial tears-require medical evaluation and rehabilitation.
The pectoralis major originates from the sternum, ribs, and clavicle and inserts into the humerus. During exercises like bench press or push-ups, especially with poor form or excessive load, microtears can occur in muscle fibers. This triggers an immune response, increasing blood flow and fluid accumulation in the tissue-resulting in swelling.
Injuries often happen during eccentric contractions-when the muscle lengthens under resistance. For example, lowering a heavy barbell during a bench press can overstress the muscle, leading to inflammation and swelling. A 2021 study in the Journal of Orthopaedic & Sports Physical Therapy found that 68% of pectoral injuries in athletes occurred during such phases.
Non-traumatic causes include infections (rare), autoimmune disorders like polymyositis, or systemic inflammation. However, these are less common and usually accompanied by fever, fatigue, or widespread muscle pain.
Swelling severity is categorized by injury grade:
| Grade | Description | Recovery Time | Common Triggers |
|---|---|---|---|
| I | Mild strain with minimal tearing; swelling limited to small areas | 1-2 weeks | Overuse, light resistance training |
| II | Partial tear; moderate swelling and bruising | 3-6 weeks | Bench press failure, sudden push motion |
| III | Complete rupture; significant swelling, loss of function | 6+ months with rehab or surgery | High-impact collision, extreme lifting |
Grade III injuries are rare but serious. They often require surgical repair and can result in permanent weakness if untreated. A 2019 case report in Orthopedic Journal of Sports Medicine documented a college football player who developed complete pectoralis major rupture after attempting a max-effort bench press, requiring tendon reattachment surgery.
Pectoral muscle swelling is frequently mistaken for heart-related issues, especially when pain radiates to the arm or shoulder. However, cardiac events rarely cause localized swelling. True pectoral swelling is visible and tender to touch, unlike angina, which typically involves pressure or tightness without physical changes.
Another confusion is equating swelling with muscle growth. Hypertrophy-the increase in muscle size due to training-develops gradually over weeks. Acute swelling from injury appears quickly, often within 24 hours, and is associated with pain and reduced movement.
A non-obvious distinction: swelling from injury can mimic a tumor. A 2020 MRI analysis in American Journal of Roentgenology showed that 12% of initial pectoral swelling cases were misdiagnosed as neoplasms due to mass-like appearance. Imaging is essential to rule out malignancy, especially in older adults or those with risk factors.
Consider a 28-year-old man who performed a heavy bench press session using 180 pounds. After the third set, he felt a sharp pop in his left chest. Within four hours, the area swelled visibly, became warm, and was painful to touch. He applied ice and rested for two days.
On day three, swelling had increased, and he noticed bruising spreading toward his armpit. An ultrasound confirmed a Grade II partial tear. He began physical therapy, avoiding overhead movements for six weeks. By week eight, swelling reduced by 70%, and strength returned to 85% of baseline.
This case illustrates that swelling doesn't always indicate severe damage-it reflects the body's healing process. But ignoring symptoms risks worsening the injury.
Seek care if swelling persists beyond five days, worsens despite rest, or is accompanied by numbness, inability to move the arm, or significant bruising. These signs suggest a more serious tear or vascular involvement.
Imaging-ultrasound or MRI-is recommended for persistent swelling. Ultrasound is effective for detecting partial tears, while MRI provides detailed images of soft tissue damage. According to the American Academy of Orthopaedic Surgeons (AAOS), early diagnosis improves outcomes by 40%.
Initial treatment follows RICE: Rest, Ice, Compression, Elevation. Apply ice for 15-20 minutes every 2-3 hours during the first 48 hours. Avoid heat, alcohol, or massage, which can increase bleeding and swelling.
After acute phase, gentle stretching and progressive resistance training restore function. A 2022 study in Physical Therapy in Sport showed that patients who began controlled exercises within seven days regained full strength 30% faster than those who delayed.
Prevention includes proper warm-up, gradual progression in weights, and maintaining balanced upper-body strength. Always perform bench presses with a spotter and avoid max lifts without supervision.