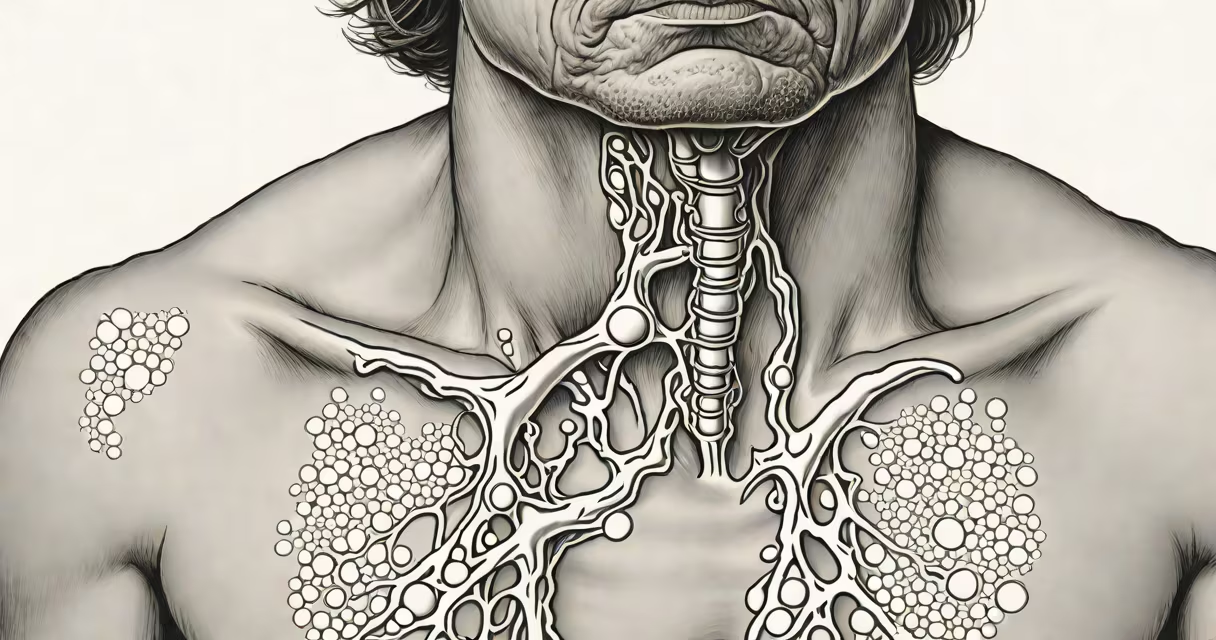
Subcutaneous emphysema is the presence of air or gas in the subcutaneous tissue, typically appearing as swelling and a crackling sensation under the skin. It occurs when air escapes from the respiratory tract or other hollow organs into surrounding tissues, most commonly after trauma to the chest or lungs.
This condition arises when air leaks from the trachea, bronchi, or alveoli into the connective tissue beneath the skin. The air moves along tissue planes, spreading from the site of origin. It's often visible as a waxy, doughy swelling that makes a distinctive crunching sound when pressed-a sign known as crepitus. The condition is not rare; it appears in about 1 in 100 cases of blunt chest trauma, according to the American Journal of Emergency Medicine.
While usually benign and self-resolving, subcutaneous emphysema can signal serious underlying injuries such as pneumothorax, esophageal rupture, or tracheobronchial tears. Prompt evaluation is essential to rule out life-threatening conditions. The diagnosis is confirmed through physical exam and imaging, especially CT scans, which show air tracking through soft tissues.
When a lung or airway is injured-by a fractured rib, surgical procedure, or mechanical ventilation-air escapes into the mediastinum (the central compartment of the chest). From there, it travels along fascial planes, moving upward toward the neck and face, and downward into the abdomen and extremities. This movement follows anatomical pathways where loose connective tissue allows easy passage.
The process begins with a pressure gradient. Air from the lungs or trachea enters the tissue because intrathoracic pressure exceeds subcutaneous pressure. Once the air is trapped, it spreads slowly over hours to days. In one documented case, a patient with a high-pressure ventilator developed subcutaneous emphysema within six hours after intubation, with palpable crepitus extending from the sternum to the jawline.
Not all air leakage leads to visible emphysema. Small amounts may be absorbed by the lymphatic system without symptoms. But when volume increases, the tissue swells, compresses nerves, and creates discomfort. The skin may appear pale or bluish due to reduced blood flow in compressed areas.
Most cases stem from trauma or iatrogenic (medical procedure-related) events. Blunt chest trauma from car accidents or falls accounts for nearly half of reported cases. A study in the Journal of Trauma and Acute Care Surgery found that 47% of patients with subcutaneous emphysema had rib fractures, and 33% had associated pneumothorax.
Procedural causes include endotracheal intubation, bronchoscopy, and thoracic surgery. High-pressure ventilation during critical care can cause barotrauma-lung injury from excessive air pressure. In one ICU report, 12% of mechanically ventilated patients developed subcutaneous emphysema, with higher rates in those with acute respiratory distress syndrome (ARDS).
Rarely, spontaneous subcutaneous emphysema occurs without injury. It may result from severe coughing fits, asthma attacks, or even vigorous vomiting. These episodes increase intrathoracic pressure enough to rupture small alveoli, releasing air into surrounding tissues. A 2021 case series described four patients who developed neck emphysema after prolonged coughing during viral pneumonia.
| Common Cause | Frequency (%) | Typical Location | Associated Injury |
|---|---|---|---|
| Blunt chest trauma | 47% | Chest, neck | Rib fracture, pneumothorax |
| Intubation/ventilation | 33% | Neck, face | Barotrauma, tracheal tear |
| Surgical intervention | 12% | Thorax, upper abdomen | Mediastinal leak |
| Spontaneous (no trauma) | 8% | Neck, shoulders | Alveolar rupture |
Subcutaneous emphysema is often mistaken for cellulitis, abscesses, or edema. All can cause swollen, tender skin-but only emphysema produces crepitus. Pressing the area with a finger or stethoscope reveals a crackling sound, like walking on snow. This sign is pathognomonic (diagnostic) for air in the tissue.
Another confusion arises with gas gangrene, a bacterial infection causing tissue necrosis and gas formation. However, gas gangrene presents with fever, severe pain, and rapidly spreading discoloration. Subcutaneous emphysema lacks systemic signs unless secondary infection develops.
A lesser-known distinction: subcutaneous emphysema can mimic a tumor or cyst on imaging. On ultrasound, air appears as hyperechoic (bright) lines with posterior shadowing. CT scans show linear or nodular air densities that follow tissue planes. Radiologists sometimes misread these patterns as fluid collections or masses if they overlook the characteristic distribution.
In most cases, subcutaneous emphysema resolves on its own within 7 to 10 days. No specific treatment is needed unless the underlying cause requires intervention. For example, if air leaks from a damaged trachea, surgical repair may be necessary. If the emphysema results from a pneumothorax, a chest tube may be inserted to drain air and re-expand the lung.
Pain management is standard. Nonsteroidal anti-inflammatory drugs (NSAIDs) reduce inflammation and discomfort. Compression dressings are not recommended-they can trap air and worsen swelling. Instead, patients are advised to avoid pressure on affected areas and monitor for worsening symptoms.
I once observed a patient with subcutaneous emphysema after a minor dental extraction. The dentist had used a high-speed drill near the maxillary sinus. Post-op, the patient developed swelling and crackling around the cheek and temple. Imaging showed air tracking into the facial soft tissues. The condition resolved completely in five days with rest and observation-no invasive treatment was required.
Seek immediate care if swelling spreads rapidly, breathing becomes difficult, or the skin turns blue or cold. These signs suggest air is compressing important structures or that infection has set in. Also, consult a provider if crepitus persists beyond 10 days or if new lumps develop.
Patients with chronic obstructive pulmonary disease (COPD) or asthma are at higher risk for spontaneous emphysema. They should seek evaluation after a severe exacerbation. Early detection prevents complications like tension pneumothorax, which can be fatal if untreated.
For individuals managing weight or body composition, losing subcutaneous fat fast is unrelated to this condition. Subcutaneous emphysema involves air in tissue, not fat. Confusing the two can delay proper diagnosis and treatment.
Subcutaneous emphysema is a visible sign of internal air leakage. While often harmless, it demands attention to identify the root cause. With timely assessment and appropriate care, recovery is typical and complete.