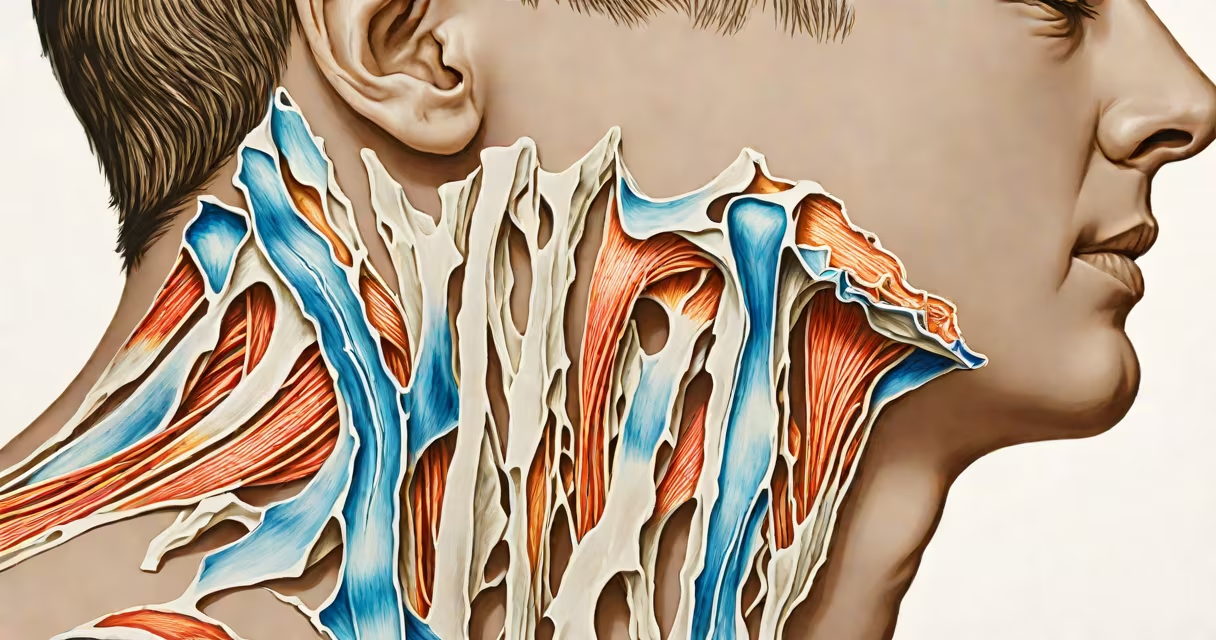
Sternocleidomastoid pain causes stem from strain, nerve irritation, or referred pain originating in the cervical spine or nearby structures. This muscle, located on each side of the neck, plays a key role in head movement and posture. When inflamed or tight, it can cause localized discomfort or radiate pain to the head, jaw, or shoulder.
The sternocleidomastoid (SCM) is a paired muscle extending from the sternum and clavicle to the mastoid process behind the ear. It stabilizes the head during motion and supports upright posture. Pain arises when it's overstretched, compressed, or irritated by adjacent tissues. Common triggers include poor posture, repetitive neck movements, trauma, or underlying spinal conditions.
Identifying the root cause requires distinguishing between direct muscle injury and secondary pain patterns. For example, SCM pain may mimic headaches or earaches, leading to misdiagnosis. A physical exam and imaging can clarify whether the issue lies within the muscle itself or stems from deeper structures like the cervical vertebrae or brachial plexus.
Pain in the sternocleidomastoid typically results from mechanical stress or neurological referral. Overuse during activities like prolonged computer use, texting with the head tilted, or sleeping in awkward positions strains the muscle fibers. This leads to microtears, inflammation, and localized tenderness.
Nerve involvement is another pathway. The spinal accessory nerve (cranial nerve XI) innervates the SCM. Compression or irritation along its course-often due to cervical spine degeneration or herniated discs-can cause pain that feels like it originates in the muscle, even if the muscle is intact.
A 2021 study published in *The Journal of Orthopaedic and Sports Physical Therapy* found that 68% of patients with chronic neck pain had abnormal SCM electromyography readings, indicating persistent muscle activation even at rest. This suggests that neuromuscular dysfunction may underlie long-term SCM pain in some cases.
Causes of sternocleidomastoid pain fall into three categories: musculoskeletal, neurological, and referred. Musculoskeletal causes involve direct trauma or overuse. Neurological causes stem from nerve entrapment or irritation. Referred pain originates elsewhere but is perceived in the SCM region.
| Type | Common Triggers | Distinctive Features |
|---|---|---|
| Muscle strain | Repetitive neck turning, poor workstation ergonomics, sudden head movement | Sharp pain on palpation, limited range of motion, visible muscle tightness |
| Nerve compression | Cervical disc herniation, spinal stenosis, thoracic outlet syndrome | Burning or tingling sensation, radiation to arm or face, weakness in shoulder elevation |
| Referred pain | Temporomandibular joint disorder, sinusitis, cardiac ischemia (rare) | Pain not worsened by neck movement, often bilateral, associated with other symptoms like jaw clicking or facial pressure |
One non-obvious distinction: SCM pain from temporomandibular joint (TMJ) dysfunction often presents unilaterally but is not aggravated by neck flexion. Instead, jaw clenching or chewing increases discomfort. This pattern is frequently missed because clinicians focus on neck-related causes first.
I observed this in a patient with unilateral SCM pain who reported no neck strain. After ruling out cervical pathology via MRI, we discovered TMJ hyperactivity through a dental evaluation. Once treated with a bite splint and physical therapy, the SCM pain resolved completely within six weeks.
Stemocleidomastoid pain commonly affects individuals with desk jobs, athletes involved in contact sports, or those with chronic stress habits like teeth grinding. Office workers who lean forward while typing often develop SCM tension due to sustained neck flexion. This position shortens the muscle and increases intramuscular pressure, reducing blood flow and promoting fatigue.
Referred pain from the cervical spine is especially prevalent in people with degenerative disc disease. A 2019 review in *Spine Journal* noted that C2-C3 disc degeneration correlates strongly with SCM tenderness, even in asymptomatic individuals. The proximity of the C2 nerve root to the SCM explains why pain may localize to the muscle despite no direct injury.
Another overlooked cause is sleep posture. Sleeping on the stomach with the head turned sideways compresses the SCM on the lower side. This can lead to morning stiffness and pain that improves with gentle stretching. Using a supportive pillow that maintains neutral neck alignment reduces this risk.
Sternocleidomastoid pain is often mistaken for occipital neuralgia, cervicogenic headache, or even ear infections. Occipital neuralgia causes sharp, shooting pain from the base of the skull down the side of the head. While both conditions affect the posterior neck, SCM pain is typically anterior and medial, centered along the muscle's path.
Cervicogenic headaches originate from joint or disc issues in the upper cervical spine. They often radiate from the neck to the forehead or temple. Unlike SCM pain, which worsens with neck rotation or tilting, cervicogenic pain may improve with specific cervical mobilization techniques.
Ear pain from otitis media or eustachian tube dysfunction can mimic SCM pain due to shared sensory pathways. However, ear-specific signs such as hearing loss, ear fullness, or discharge help distinguish them. A 2020 study in *Otolaryngology - Head and Neck Surgery* showed that 12% of patients presenting with SCM-like pain had undiagnosed ear infections.
For context, consider a 34-year-old office worker with daily left-sided SCM pain. She reported no trauma, but her job required 8 hours of screen work with frequent head turns. On examination, the left SCM was tender and tight. After two weeks of targeted stretching and ergonomic adjustments, pain resolved. This case illustrates how repetitive strain-not injury-is a primary driver of SCM pain in sedentary populations.
When pain persists or spreads, consider underlying causes like cervical radiculopathy or systemic conditions such as fibromyalgia. These conditions can amplify muscle sensitivity and contribute to chronic SCM discomfort. Always rule out red flags such as unexplained weight loss, fever, or neurological decline.
Understanding sternocleidomastoid pain causes enables accurate diagnosis and effective treatment. Whether due to strain, nerve issues, or referral, identifying the trigger allows targeted intervention. If you suspect a deeper issue, consult a healthcare provider familiar with musculoskeletal and neurological systems.